

Endoscopic Sleeve Gastroplasty (ESG): A Patient Information Guide

Endoscopic Sleeve Gastroplasty (ESG) is a minimally invasive, incision‑free weight‑loss procedure designed for adults with obesity who have not achieved sufficient results through diet, exercise, or medical therapy. It reduces stomach volume using internal sutures placed through an endoscope, helping patients feel full sooner and eat less. ESG has gained global acceptance as a safe, effective option for selected patients seeking a non‑surgical alternative to bariatric surgery.
What ESG Is and How It Works
ESG uses a flexible endoscope inserted through the mouth into the stomach. A suturing device attached to the endoscope places stitches inside the stomach wall, creating large folds that reshape the stomach into a narrow, sleeve‑like tube. This reduces stomach capacity by approximately 70–80%, limiting food intake and enhancing early satiety.
Unlike surgical sleeve gastrectomy, no stomach tissue is removed, and there are no external incisions. The procedure is performed under general anesthesia.
Who ESG Is For
ESG may be appropriate for adults who:
- Have a BMI ≥ 30 (or ≥ 27.5 for certain ethnic groups).
- Have not achieved sustained weight loss through lifestyle changes.
- Prefer a minimally invasive option or do not qualify for traditional bariatric surgery.
ESG is not suitable for individuals with:
- Large hiatal hernias
- Active gastrointestinal bleeding, gastritis, or peptic ulcer disease
- Certain anatomical or medical contraindications identified during screening
Expected Benefits
Weight Loss
Clinical guidance shows ESG can lead to:
- 18–20% total body weight loss within 12–24 months when combined with lifestyle changes.
- ~40% excess weight loss reported in some patient information leaflets.
Improvement in Obesity‑Related Conditions
ESG may help improve:
- Type 2 diabetes
- High blood pressure
- High cholesterol
- Sleep apnea
- Joint pain
- Metabolic dysfunction–associated steatotic liver disease (MASLD/MASH)
Recovery Advantages
- No external cuts or stapling
- Shorter hospital stay (often same day or 1 night)
- Faster return to daily activities compared to surgical bariatric procedures
The Procedure Step‑by‑Step
- General anesthesia is administered.
- The endoscope is passed through the mouth into the stomach.
- A suturing device places stitches along the stomach wall.
- These stitches create folds that narrow the stomach into a sleeve shape.
- The procedure reduces stomach volume by 70–80%.
Total procedure time is typically under 90 minutes.
Risks and Possible Complications
ESG is considered safe, but all medical procedures carry risks. Reported complications include:
- Pain, nausea, or vomiting in the first few days (usually controlled with medication)
- Sore throat from the endoscope
- Aspiration (food or fluid entering the airway)
- Abdominal pain or dehydration
- Bleeding (around 1 in 500 cases)
- Peritonitis or abscess formation
- Pneumothorax (air in the chest cavity)
- Rare perforation of the stomach or esophagus (around 1 in 5000 cases)
Most symptoms resolve within days, and serious complications are uncommon.
Recovery and Aftercare
Hospital Stay
- Many patients go home the same day; others may stay one night depending on recovery.
Diet Progression
Your care team will guide you through:
- Clear liquids
- Full liquids
- Soft foods
- Gradual return to solid foods
Lifestyle Commitment
Long‑term success requires:
- Permanent dietary changes
- Regular physical activity
- Behavioral therapy when recommended
- Ongoing medical follow‑up
Is ESG Reversible?
NICE notes that ESG is potentially reversible because no stomach tissue is removed. However, some clinical sources emphasize that the stomach cannot always be restored to its exact original shape, and sutures may not be fully reversible in practice. (This is an inference based on differences in clinical descriptions.)
Questions to Discuss With Your Healthcare Team
NICE recommends patients consider:
- How many appointments are required
- Expected benefits and likelihood of achieving them
- Risks and their probabilities
- Whether hospitalization is needed
- Alternatives if ESG is not suitable
- What happens if complications occur or results are insufficient
Summary
Endoscopic Sleeve Gastroplasty is a safe, minimally invasive weight‑loss procedure that reduces stomach volume using internal sutures. It offers meaningful weight loss and improvement in obesity‑related conditions with faster recovery than surgical options. ESG is best suited for motivated patients willing to commit to long‑term lifestyle changes and regular follow‑up.
References
- University Hospitals Coventry & Warwickshire. Endoscopic Sleeve Gastroplasty – Patient Information Leaflet. 2024.
- Mayo Clinic. Endoscopic Sleeve Gastroplasty – Tests & Procedures Overview. 2026.
- National Institute for Health and Care Excellence (NICE). Endoscopic Sleeve Gastroplasty for Obesity – Public Information (HTG711). Updated Feb 2024.

Cancer & Obesity : Understanding the Link in South Africa
When most people think about obesity, conditions such as diabetes, high blood pressure and heart disease usually come to mind. Cancer is mentioned far less often.
However, excess body fat is now recognised as an important risk factor for several cancers. This does not mean that every person living with obesity will develop cancer, or that body weight is the only reason cancer occurs. It means that, over time, excess body fat can create biological conditions that make certain cancers more likely to develop.
This matters greatly in South Africa, where obesity has become a serious public-health concern. It also needs to be discussed carefully. Obesity is a complex chronic disease, not simply the result of laziness or a lack of willpower. Genetics, medication, income, food prices, mental health, working conditions, neighbourhood safety and access to healthcare can all influence a person’s weight.
Why this issue matters in South Africa
More than half of South Africa’s adult population is living with overweight or obesity. Among women, the figure is more than two-thirds. WHO data separately estimate that approximately 30.8% of South African adults were living specifically with obesity in 2022. South Africa had one of the highest adult obesity levels in the African region.
The National Department of Health has described obesity as an urgent public-health crisis. Its national strategy recognises that the problem cannot be solved by telling people to “eat less and move more”. Food systems, advertising, poverty, limited access to healthy food, unsafe neighbourhoods and a lack of suitable opportunities for physical activity all affect the choices available to South Africans.
Cancer is also placing a substantial burden on the country. The International Agency for Research on Cancer estimated that South Africa had approximately 101,598 new cancer cases and 55,356 cancer deaths in 2024. Breast cancer, colorectal cancer and cancer of the uterus were among the significant cancers affecting South Africans.
Several cancers associated with excess body fat are already present in meaningful numbers. The 2024 estimates included:
- 13,338 breast cancer cases;
- 6,816 colorectal cancer cases;
- 2,263 pancreatic cancer cases;
- 1,779 cancers of the body of the uterus; and
- 1,143 kidney cancer cases.
These figures represent the estimated total number of cases and should not be interpreted as the number directly caused by obesity. Cancer usually develops through a combination of factors, including age, genetics, infections, tobacco use, alcohol, environmental exposures and chance cellular changes.
What do doctors mean by obesity?
Obesity is a medical condition involving an unhealthy amount or distribution of body fat.
Body mass index, usually called BMI, is commonly used as a screening tool. It is calculated by dividing a person’s weight in kilograms by the square of their height in metres:
BMI = weight in kilograms ÷ height² in metres
For adults, a BMI from 25 to 29.9 is commonly classified as overweight, while a BMI of 30 or above is classified as obesity. However, BMI does not directly measure body fat and cannot, on its own, provide a complete picture of an individual’s health. Muscle mass, waist circumference, fat distribution, age and metabolic health also matter.
The number on a scale is therefore only one part of the picture. Two people with the same BMI may have different amounts of muscle, different levels of abdominal fat and very different health risks.
Which cancers are linked to obesity?
Research reviews have linked excess body fat with an increased risk of at least 13 types of cancer.
These include:
- breast cancer after menopause;
- colorectal cancer;
- endometrial cancer, which affects the lining of the uterus;
- kidney cancer;
- pancreatic cancer;
- liver cancer;
- gallbladder cancer;
- ovarian cancer;
- thyroid cancer;
- adenocarcinoma of the oesophagus;
- cancer of the upper part of the stomach;
- multiple myeloma; and
- meningioma, a tumour arising in the membranes surrounding the brain and spinal cord.
The increase in risk is not equal for every cancer.
One of the strongest associations is seen with endometrial cancer. According to the United States National Cancer Institute, people with severe obesity have approximately seven times the risk of certain estrogen-related endometrial cancers compared with people in a healthy weight range. The relationship is also particularly strong for oesophageal adenocarcinoma.
For breast cancer, the relationship with body weight depends partly on age and hormonal status. The clearest established association is between excess body fat and breast cancer after menopause.
How can body fat influence cancer growth?
Body fat does more than store excess energy. Fat tissue is biologically active. It produces hormones and chemical signals that can affect inflammation, metabolism, immune function and cell growth.
There is no single pathway through which obesity causes every cancer. Different biological processes may be involved in different parts of the body.
Increased estrogen levels
After menopause, the ovaries produce much less estrogen. Fat tissue then becomes an important source of estrogen in the body.
Higher amounts of body fat can result in higher estrogen exposure. Estrogen can stimulate the growth of certain hormone-sensitive cells, helping to explain part of the association between obesity and postmenopausal breast, endometrial and ovarian cancers.
Insulin and growth signals
People living with obesity may develop insulin resistance. This means that the body does not respond to insulin as effectively as it should, so the pancreas produces more insulin to compensate.
Higher levels of insulin and insulin-like growth factor 1, known as IGF-1, can encourage some cells to grow and divide. Increased insulin and IGF-1 levels have been associated with colorectal, breast, ovarian, thyroid and endometrial cancers, among others.
This does not mean that insulin itself suddenly creates a tumour. Rather, persistently altered metabolic signals may contribute to an environment in which abnormal cells are more likely to survive or multiply.
Long-term inflammation
Obesity can be accompanied by chronic, low-level inflammation.
Inflammation is normally part of the body’s healing and defence system. When it continues over a long period, however, it can damage cells and alter the signals that control cell growth. Chronic inflammation may therefore contribute to the development and progression of some tumours.
Changes in hormones released by fat cells
Fat cells release signalling substances called adipokines.
One of these, leptin, generally rises as body fat increases and may encourage abnormal cell growth under certain conditions. Another, adiponectin, may have protective effects against uncontrolled cell growth but is often present at lower levels in people living with obesity.
Researchers are continuing to investigate how these hormones interact with the immune system, metabolism and tumour cells.
Does obesity mean that cancer is inevitable?
No.
Obesity increases risk, but it does not make cancer unavoidable. Many people living with obesity never develop cancer, while people in a healthy weight range can still be diagnosed with cancer.
Cancer is a complex group of diseases. Age, inherited genetic variants, tobacco, alcohol, infections, radiation, environmental exposures and random changes during cell division can all contribute to its development. WHO estimates that a substantial proportion of cancers can be prevented by reducing known risks and implementing evidence-based prevention strategies, but no lifestyle can offer complete protection.
The purpose of discussing obesity and cancer should therefore be prevention and support, not blame.
Can losing weight reduce cancer risk?
Research suggests that maintaining a healthy weight and avoiding excessive weight gain may reduce the risk of several cancers.
Some observational studies have found lower rates of breast, endometrial, colorectal and prostate cancers among people with obesity who lost weight. For example, intentional weight loss of more than 5% was associated with a lower risk of obesity-related cancers in one study of postmenopausal women.
A 5% reduction does not need to be dramatic. For a person weighing 100 kilograms:
100 kg × 5% = 5 kg
Their weight after losing 5% would therefore be 95 kilograms.
However, the evidence must be interpreted carefully. Much of it comes from observational studies, which cannot prove that weight loss alone caused the reduction in cancer risk. Randomised trials have not yet provided a precise answer about how much weight a person must lose to reduce the risk of each cancer.
The realistic goal is not rapid or extreme weight loss. It is a sustainable improvement in eating patterns, physical activity, metabolic health and overall wellbeing.
Practical steps that can help
Cancer prevention does not require expensive imported foods, a gym membership or an extreme diet. Small, repeatable habits are more useful than a strict programme that lasts only a few weeks.
Build meals around affordable whole foods
South African households can make healthier meals using familiar foods such as dry beans, lentils, split peas, vegetables, fruit, oats, sorghum, wholegrain bread, brown rice, mealie meal and samp.
Beans, lentils and other pulses are useful because they provide fibre and can replace part of the meat in stews, soups and curries. Seasonal fruit and vegetables are often more affordable than out-of-season produce.
CANSA recommends meals that include fruit, non-starchy vegetables, wholegrains and legumes, while limiting highly processed foods and drinks that are high in sugar, salt and fat.
A practical meal could be as simple as samp and beans with vegetables, lentil curry with brown rice, or pap served with beans, spinach and a moderate portion of lean protein.
Drink more water and fewer sugary drinks
Sugar does not directly “feed cancer” in the simplistic way often claimed online. Every cell in the body uses glucose.
The more relevant concern is that sugary drinks can provide large amounts of energy without creating much fullness, which can contribute to weight gain over time. South Africa introduced its Health Promotion Levy on sugar-sweetened beverages in 2018 as part of broader attempts to improve the food environment.
Water should be the everyday drink wherever clean drinking water is safely available.
Increase fibre
Foods containing fibre include beans, lentils, wholegrains, vegetables, fruit, nuts and seeds.
Fibre supports digestive health and is particularly relevant to colorectal-cancer prevention. CANSA advises South Africans to increase fibre intake and reduce processed meat consumption as part of lowering colorectal-cancer risk.
Changes should be gradual, especially for someone who currently eats little fibre. Drinking sufficient water is also important when increasing fibre intake.
Move in ways that are realistic
Physical activity does not need to mean running or joining a gym. Brisk walking, dancing, gardening, active housework, cycling and community sport can all contribute.
WHO recommends that adults aim for at least 150 minutes of moderate-intensity activity each week, or 75 minutes of vigorous activity. Muscle-strengthening activity is recommended on at least two days per week.
One way to reach the basic target is:
30 minutes × 5 days = 150 minutes per week
Someone who is currently inactive can begin with shorter periods, such as ten minutes at a time, and increase gradually. Some movement is better than none.
A person with heart disease, severe obesity, mobility limitations or another medical condition should obtain professional advice before beginning strenuous exercise.
Avoid crash diets
Very restrictive diets may produce quick results, but they can be difficult to maintain and may lead to repeated weight loss and regain.
A healthier approach is to make changes that can continue in ordinary life: cooking at home more often, reducing portion sizes gradually, increasing vegetables and legumes, replacing sugary drinks with water and finding a form of movement that is enjoyable and accessible. The World Cancer Research Fund recommends small, achievable changes rather than fad diets.
Ask for medical support when needed
Obesity is a chronic disease and may require professional treatment.
A doctor can assess blood pressure, blood glucose, cholesterol, liver health, medication use and other factors that may be contributing to weight gain. Depending on a person’s circumstances, appropriate care may include support from a registered dietitian, psychological support, structured lifestyle treatment, medication or metabolic surgery.
South Africa’s obesity response increasingly recognises the need for care to be available through community and primary-health services, rather than relying only on individual willpower.
Weight management does not replace cancer screening
Living healthily can reduce risk, but it cannot guarantee that cancer will not develop.
People should still attend appropriate cancer screening and seek medical attention for persistent or unusual symptoms. These may include a new lump, unexplained bleeding, lasting changes in bowel habits, difficulty swallowing or unexplained weight loss.
South Africans should speak to a healthcare professional about screening appropriate to their age, sex, family history and personal risk factors. Early detection can improve treatment options and outcomes for many cancers.
What about people who already have cancer?
A person receiving cancer treatment should not begin a strict weight-loss programme without speaking to their oncology team.
Cancer and its treatment can cause weight gain in some people and dangerous loss of weight or muscle in others. Nutritional needs may also change during chemotherapy, radiation therapy or surgery.
Anyone having difficulty with weight during treatment should ask their cancer-care team or a registered dietitian for personalised guidance.
A conversation without shame
Weight is a sensitive subject, especially in a country where many people face food insecurity while obesity is increasing at the same time.
Some families may have access to enough calories but not consistently to affordable, nutritious food. Others live in areas where outdoor exercise is unsafe or where long commuting hours leave little time for meal preparation and physical activity.
This is why obesity cannot be treated only as an individual failure. South Africa’s national strategy places personal behaviour within a wider system that includes family, schools, workplaces, food companies, healthcare, community safety, policy and socioeconomic conditions.
Shame rarely helps someone improve their health. Respectful information, realistic options and access to proper care are far more useful.
Final thoughts
The connection between obesity and cancer is real, but it is not simple.
Excess body fat can affect estrogen, insulin, inflammation and other biological signals that influence how cells grow. This helps explain why obesity is associated with cancers of the breast after menopause, bowel, uterus, kidney, pancreas and several other organs.
For South Africa, the challenge is particularly important because the country faces high levels of obesity alongside a growing burden of noncommunicable diseases.
The answer is not a perfect body or a crash diet. It is a long-term effort to make nutritious food, safe physical activity and evidence-based healthcare more accessible to everyone.
At an individual level, regular movement, balanced meals, less sugary and highly processed food, and professional support where necessary can help lower cancer risk and improve health more broadly. These steps reduce risk; they do not offer a guarantee.
References
- World Health Organization. South Africa: Applying the Lessons Learned from Tackling HIV to Accelerate Action on Obesity. 4 March 2025.
- World Health Organization. South Africa Country Health Data: Adult Obesity. 2022 estimate.
- South African National Department of Health. Strategy for the Prevention and Management of Obesity in South Africa 2023–2028.
- International Agency for Research on Cancer. Global Cancer Observatory: South Africa Fact Sheet, GLOBOCAN 2024. Published July 2026.
- National Cancer Institute. Obesity and Cancer Fact Sheet. Updated January 2025.
- World Cancer Research Fund International. Weight, Obesity and Cancer.
- World Health Organization. Physical Activity Recommendations.
- Cancer Association of South Africa. THINK Before You Eat & Drink. Updated September 2025.
- Cancer Association of South Africa. Colorectal Cancer: The Power of Balance, Fibre and Gut Health. 2025.
This article is intended for general education and does not replace medical advice, diagnosis or treatment from a qualified healthcare professional.

Why Bariatric Surgery Still Has the Stronger Long-Term Case Than GLP-1 Weight-Loss Drugs
GLP-1 weight-loss medications have changed the conversation around obesity treatment. That is a good thing. For many people, medicines such as semaglutide have helped reduce appetite, improve blood sugar, lower weight, and in some high-risk patients, reduce cardiovascular events. Tirzepatide, often discussed in the same public conversation although it is technically a dual GIP/GLP-1 medication, has produced even stronger weight-loss results in trials.

So this is not an “injections don’t work” article. They do work.
The real question is different: what happens over the long term?
Because long-term weight loss is not about what happens for a few months while motivation is high and treatment is new. It is about what still holds five years later. Ten years later. Twenty years later. It is about diabetes control, heart risk, medication burden, quality of life, and whether the treatment keeps working when real life becomes messy.
That is where bariatric surgery still has the stronger case for suitable patients.
GLP-1 drugs are powerful, but they are treatment-dependent
The best GLP-1 results are impressive. In the STEP 5 trial, semaglutide 2.4 mg produced an average weight loss of 15.2% at 104 weeks, compared with 2.6% on placebo [1]. In the SELECT trial, semaglutide produced sustained weight loss over four years and reduced major cardiovascular events by 20% in people with overweight or obesity and established cardiovascular disease, but without diabetes [2].
That deserves respect.
But the important detail is this: the benefit depends heavily on continued treatment.
In the STEP 1 extension study, participants who had lost 17.3% of their body weight on semaglutide regained 11.6 percentage points after stopping treatment. Put simply, they regained about two-thirds of the weight they had lost after the medicine was withdrawn: 11.6 divided by 17.3 equals roughly 67% [3].
Tirzepatide shows the same basic pattern. In the SURMOUNT-4 withdrawal trial, people who continued tirzepatide maintained and added to their weight loss, while those who stopped treatment regained a substantial amount of weight [4].
That does not mean GLP-1 medicines are bad. It means they behave like chronic medication. Like blood-pressure tablets, cholesterol medication, or diabetes medication, they work while they are being used. Stop the treatment, and the biology that drove the disease often returns.
For some patients, that is perfectly acceptable. But it changes the long-term conversation.
Real life is not a clinical trial
Clinical trials are controlled environments. Patients are selected, monitored, encouraged, followed up, and supplied with medication. Real life is different. People stop medication because of side effects, cost, supply problems, loss of motivation, pregnancy planning, travel, family pressure, work stress, or simply because weekly injections become too much.
A large real-world JAMA Network Open cohort study found that among adults using GLP-1 receptor agonists for overweight or obesity, 64.8% of patients without type 2 diabetes discontinued within one year. By two years, that figure was 84.4% [5].
That is a major long-term weakness.
A treatment cannot deliver long-term benefit if most people cannot stay on it. And this is where bariatric surgery has a different profile. Surgery is not easy, and it is not a shortcut, but once the operation is done, the main metabolic intervention has happened. The patient still needs follow-up, nutrition support, movement, protein, vitamins, and behaviour change. But they are not relying on a weekly prescription to keep the entire treatment active.
Bariatric surgery has the long-term data GLP-1 drugs do not yet have
This is the heart of the argument.
Modern GLP-1 medications are promising, but they do not yet have the same depth of 10-, 15-, and 20-year obesity outcome data that bariatric surgery has. Bariatric surgery has been studied for decades, across weight loss, diabetes, cardiovascular outcomes, cancer risk, survival, and quality of life.
The 2022 ASMBS/IFSO guidelines state that metabolic and bariatric surgery produces significant and durable weight loss, with durability demonstrated at 5, 10, and 20 years after surgery [6].
A 12-year study of Roux-en-Y gastric bypass published in the New England Journal of Medicine found that at 10 years, 72% of patients had maintained at least 20% weight loss from baseline [7]. That is a very different type of result from “weight loss while on medication.” It is durable weight loss years after a once-off anatomical and metabolic intervention.
The Swedish Obese Subjects study also found that bariatric surgery was associated with long-term weight loss and reduced overall mortality [8]. Another long-term analysis from the same study found fewer cardiovascular deaths and cardiovascular events in the surgery group compared with usual care [9].
A 2021 Lancet meta-analysis reported that metabolic-bariatric surgery was associated with substantially lower all-cause mortality and longer life expectancy compared with usual non-surgical obesity care [10].
That is why surgery still stands apart. The long-term evidence is not just about kilos lost. It is about disease trajectory.
Diabetes is where surgery becomes especially hard to beat
For patients with obesity and type 2 diabetes, bariatric surgery is not simply a weight-loss operation. It is metabolic treatment.
The STAMPEDE trial compared intensive medical therapy alone with intensive medical therapy plus bariatric surgery in patients with type 2 diabetes. At five years, surgery plus medical therapy was superior for glycaemic control, weight reduction, medication reduction, and quality-of-life measures [11].
That matters because diabetes is not a cosmetic disease. It affects the heart, kidneys, eyes, nerves, circulation, and long-term survival. If a treatment can reduce weight and reduce the need for diabetes medication while improving metabolic control, it deserves serious attention.
GLP-1 drugs also improve diabetes and cardiovascular risk. That is not in dispute. But again, the long-term issue is dependence. The medication must usually continue. Surgery, when successful and properly supported, can create a lasting metabolic shift that reduces the need for ongoing medication in many patients.
Surgery is not magic — and pretending it is would be dishonest
Bariatric surgery is not the right answer for everyone.
It is surgery. It carries risk. Patients need proper assessment, an experienced surgical team, anaesthetic evaluation, psychological readiness, nutrition support, and long-term follow-up. There can be complications. There can be reflux, strictures, ulcers, gallstones, nutritional deficiencies, weight regain, or the need for revision surgery. Lifelong supplementation and monitoring are part of responsible bariatric care.
Modern bariatric surgery is much safer than many people assume, but it should never be presented casually. Current evidence reports mortality around 0.1% to 0.13% and major complication rates under 5% in accredited centres [12]. Low risk is not the same as no risk.
The patient also has to participate. Surgery changes the biology, but it does not remove responsibility. Protein intake matters. Movement matters. Follow-up matters. Supplements matter. Eating patterns matter.
The difference is that surgery often makes the lifestyle change more achievable because it changes hunger, satiety, portion size, gut hormone responses, and metabolic signalling. It is not just “eat less.” It helps the body respond differently.
The fairest answer is not surgery versus medication — it is choosing the right tool
There are patients for whom GLP-1 medication may be the better first step. Someone with a lower BMI, someone not ready for surgery, someone with high surgical risk, someone needing to lose weight before an operation, or someone who has regained weight after surgery may benefit greatly from medication.
There are also patients for whom surgery may be the stronger long-term option: people with severe obesity, obesity-related diabetes, sleep apnoea, hypertension, fatty liver disease, mobility limitations, or repeated failed attempts at non-surgical weight loss.
The strongest future model may not be “surgery or medication.” It may be surgery and medication, used intelligently at different stages of the disease.
But if the question is blunt — which treatment currently has the stronger long-term evidence for suitable patients with severe obesity? — bariatric surgery still has the edge.
Not because GLP-1 drugs are weak.
Because bariatric surgery has something the drugs are still building: decades of durability data, long-term metabolic outcomes, survival evidence, and a treatment effect that does not disappear simply because a prescription is stopped.
GLP-1 medications have opened an important new chapter in obesity care. Bariatric surgery remains the chapter with the longest follow-up and the strongest long-term track record.
For the right patient, in the right hands, with the right follow-up, surgery is still the most proven long-term intervention we have.
Reference map for the numbered sources in the article
[1] The STEP 5 semaglutide trial reported mean body-weight change of −15.2% at 104 weeks with semaglutide versus −2.6% with placebo.
[2] The SELECT semaglutide analysis reported sustained weight loss up to 208 weeks and a 20% reduction in major adverse cardiovascular events in the SELECT cardiovascular outcomes trial population.
[3] The STEP 1 extension found that after semaglutide withdrawal, participants regained 11.6 percentage points of a prior 17.3% mean weight loss by week 120.
[4] The SURMOUNT-4 withdrawal trial found that stopping tirzepatide led to substantial weight regain, while continued treatment maintained and augmented weight loss.
[5] The JAMA Network Open real-world cohort study reported 64.8% one-year discontinuation among patients without type 2 diabetes and 84.4% discontinuation by two years.
[6] The 2022 ASMBS/IFSO guidelines state that bariatric surgery has durable outcomes over 5, 10, and 20 years and is superior to non-surgical methods for significant durable weight loss and obesity-related comorbidity improvement.
[7] The NEJM 12-year gastric bypass study reported that at 10 years, 72% of Roux-en-Y gastric bypass patients had maintained at least 20% weight loss from baseline.
[8] The Swedish Obese Subjects mortality study found bariatric surgery was associated with long-term weight loss and decreased overall mortality.
[9] The Swedish Obese Subjects cardiovascular analysis found bariatric surgery was associated with fewer cardiovascular deaths and lower incidence of cardiovascular events than usual care.
[10] The 2021 Lancet meta-analysis found metabolic-bariatric surgery was associated with lower all-cause mortality and longer life expectancy than usual obesity care.
[11] The STAMPEDE five-year trial found bariatric surgery plus intensive medical therapy was superior to intensive medical therapy alone for glycaemic control and weight reduction in patients with type 2 diabetes and BMI 27–43.
[12] Modern bariatric surgery safety data report mortality around 0.1% to 0.13% and major complication rates under 5% at accredited centres

Alcohol After Bariatric Surgery: General Do’s and Don’ts
Bariatric surgery changes more than the size of the stomach. It changes the way the body handles food, fluids, sugar, medication, and alcohol. For this reason, alcohol after bariatric surgery needs to be approached carefully, even when the person is not misusing alcohol and only wants to drink socially from time to time.
This article is not about alcohol abuse. It is about general alcohol use after bariatric surgery, including what patients should understand, what to avoid, and how to make safer decisions after procedures such as gastric bypass and sleeve gastrectomy.
Why Alcohol Feels Stronger After Bariatric Surgery
After bariatric surgery, especially Roux-en-Y gastric bypass and sleeve gastrectomy, alcohol can enter the bloodstream faster than it did before surgery. This means a person may feel the effects of alcohol much sooner, with less alcohol than they previously needed. The American Society for Metabolic and Bariatric Surgery notes that alcohol is absorbed more quickly after bariatric surgery and that patients may have higher alcohol levels for longer after drinking.
In simple terms, one drink after bariatric surgery may not feel like one drink used to feel before surgery. A patient who previously tolerated two glasses of wine may find that one glass now causes dizziness, poor coordination, sleepiness, flushing, or rapid intoxication.
Research discussed in the Bariatric Times article also explains that alcohol pharmacokinetics are significantly altered after both gastric bypass and sleeve gastrectomy, with alcohol levels rising faster and reaching a higher peak than in people who have not had metabolic and bariatric surgery.
Alcohol Is Not Forbidden for Everyone Forever, But It Must Be Treated Differently
Not every patient will be told to avoid alcohol for life. However, almost every bariatric patient should treat alcohol differently after surgery.
The key issue is not only intoxication. Alcohol can also affect weight loss, hydration, blood sugar control, food choices, sleep, liver health, and long-term metabolic goals. Alcohol contains calories but provides no meaningful nutrition. This becomes more important after bariatric surgery because patients have limited stomach capacity and need to prioritise protein, hydration, vitamins, and nutrient-dense foods.
The World Health Organization states that alcoholic beverages contain ethanol, which is a psychoactive and toxic substance with dependence-producing properties. That does not mean every patient who drinks socially has a problem, but it does mean alcohol should be treated as a substance with real physical effects, not as an ordinary drink.
The First Rule: Do Not Drink Alcohol Too Soon After Surgery
The safest general principle is: avoid alcohol during the early recovery and rapid weight-loss phase unless your bariatric team has specifically cleared you.
The early months after surgery are when the body is healing, the stomach is sensitive, food intake is limited, and hydration can already be challenging. Alcohol can irritate the stomach, worsen dehydration, add empty calories, lower inhibitions around food choices, and increase the risk of nausea or vomiting.
Many bariatric programmes recommend avoiding alcohol for a prolonged period after surgery, often during the first months or the first year, but exact advice can vary by surgeon, procedure, medical history, and recovery progress. The Bariatric Times article makes clear that bariatric teams should educate patients about alcohol risks before surgery and refresh that education after surgery because the risk is long-term, not only immediate.
Do: Ask Your Bariatric Team When Alcohol Is Safe for You Personally
The correct timing is not the same for every person. A patient who had a straightforward sleeve gastrectomy, stable blood sugar, no reflux, no liver disease, and excellent nutritional intake may receive different advice from a patient who had gastric bypass, complications, ulcers, diabetes, or a history of alcohol problems.
Before drinking again, patients should ask:
Has my stomach healed enough?
Am I still struggling with nausea, reflux, ulcers, or vomiting?
Am I meeting my protein goals?
Am I taking my supplements properly?
Am I staying hydrated?
Am I still in the rapid weight-loss phase?
Am I on medication that interacts with alcohol?
This is important because alcohol can interact with pain medication, sedatives, antidepressants, sleeping tablets, diabetes medication, and other prescriptions.
Don’t: Test Your Tolerance in Public
A common mistake is assuming that alcohol tolerance after surgery will be the same as before surgery. It usually is not.
Patients who decide to drink after being cleared by their medical team should not test their new tolerance at a wedding, restaurant, party, braai, corporate function, or family event. The first experience after surgery should be approached cautiously, ideally in a safe environment, with trusted people nearby, and with no need to drive.
The reason is simple: alcohol may affect you faster than expected. The ASMBS patient guidance warns that alcohol reaches the bloodstream faster and remains at higher levels for longer after bariatric surgery.
Do: Start Very Small
After bariatric surgery, “moderate drinking” may need to be redefined. A standard serving may be too much for some patients.
A cautious approach would be to take a few sips, wait, and observe how the body responds. Patients should not drink quickly. They should avoid drinking on an empty stomach, and they should stop immediately if they feel lightheaded, flushed, sleepy, unsteady, nauseous, or unusually intoxicated.
This is not about fear. It is about respecting the new anatomy and the new way the body processes alcohol.
Don’t: Drink on an Empty Stomach
Drinking on an empty stomach can intensify the effect of alcohol. After bariatric surgery, this can be even more noticeable because the stomach is smaller and alcohol may pass through more quickly.
Patients should first make sure they have eaten appropriate bariatric-friendly food, especially protein-based food, before considering alcohol. However, they should still follow their bariatric team’s instructions about separating fluids and meals, because many programmes advise patients not to drink fluids immediately before, during, or after meals.
Do: Choose Lower-Risk Options
When a patient has been cleared to drink, the better choice is usually a small, simple drink that can be consumed slowly.
Better options may include:
a small glass of dry wine
a light drink served slowly
a small measured serving rather than a free-poured drink
Riskier options usually include:
cocktails high in sugar
sweet liqueurs
creamy alcoholic drinks
carbonated alcoholic drinks
shots
double spirits
high-alcohol craft drinks
drinking games or rounds
Sugary drinks can add calories quickly and may contribute to unpleasant symptoms in some bariatric patients. Alcohol itself also provides calories without protein, fibre, vitamins, or minerals.
Don’t: Drink Carbonated Alcoholic Beverages Without Medical Guidance
Many bariatric patients are advised to avoid or limit carbonated beverages, especially early after surgery. Carbonation can cause bloating, discomfort, gas pressure, and stomach irritation. This may make drinks such as beer, cider, sparkling wine, champagne, alcoholic seltzers, and mixers like soda or tonic water less suitable for some patients.
This is especially relevant when the patient is still adjusting to smaller portions and slower drinking patterns.
Do: Watch Your Weight-Loss Goals
Alcohol can slow progress after bariatric surgery in several ways.
First, alcohol contains calories. Second, it can reduce self-control around food choices. Third, it may increase snacking. Fourth, it can affect sleep quality, and poor sleep can make weight management more difficult. Fifth, alcohol may displace healthier choices such as water, protein, and planned meals.
The Bariatric Times article notes that substance use after surgery can affect postoperative adherence, including appointment attendance, hydration, supplement routines, food choices, meal planning, portion control, physical activity, and weight outcomes.
For patients who want the best long-term result from surgery, alcohol should never become a regular source of calories.
Don’t: Drive After Drinking, Even After “Only One”
This point is extremely important. After bariatric surgery, a person may be impaired after a smaller amount of alcohol than expected. Because alcohol may be absorbed faster and reach higher levels, “I only had one drink” may not mean the same thing anymore.
Patients should avoid driving after drinking alcohol. They should also be careful with stairs, swimming, exercise, childcare, cooking, and any activity requiring coordination or judgement.
Do: Pay Attention to Changes Over Time
Alcohol sensitivity after surgery is not only an issue in the first few months. Some alcohol-related problems may appear later. The Bariatric Times article explains that the higher-risk period for post-bariatric alcohol problems appears to begin at least around two years after surgery in some research, although some studies observed risk earlier.
Again, this does not mean every patient will develop a problem. But it does mean patients should continue paying attention long after the surgery date.
Warning signs may include:
drinking more often than planned
feeling alcohol more strongly than before
using alcohol to cope with stress
drinking alone more often
choosing alcohol instead of meals
missing supplements or hydration goals because of drinking
weight-loss progress slowing because of alcohol calories
family or friends expressing concern
These signs do not mean a person has failed. They mean it is time to pause, speak to the bariatric team, and adjust.
Don’t: Use Alcohol as a Coping Tool
After bariatric surgery, food can no longer be used in the same way it may have been used before. Some patients feel emotionally unsettled when they lose their old coping mechanism. Alcohol should not become the replacement.
The healthier route is to build new coping tools before they are urgently needed. These can include walking, counselling, support groups, journaling, prayer, hobbies, structured routines, better sleep, or regular check-ins with the bariatric team.
The Bariatric Times article specifically encourages education, monitoring, and healthy coping strategies after surgery because some patients may develop new substance-related difficulties even without a previous history.
Do: Keep Hydration First
Hydration is one of the foundations of recovery and long-term bariatric success. Alcohol can contribute to dehydration, and dehydration can already be a risk after bariatric surgery because patients drink smaller amounts at a time.
If alcohol is used at all, water intake should remain a priority. Patients should avoid drinking alcohol when they are already dehydrated, vomiting, exercising heavily, recovering from illness, or struggling to meet daily fluid targets.
Don’t: Drink While Taking Certain Medications
Alcohol can interact with many medications, including pain medication, sleeping tablets, anxiety medication, antidepressants, sedatives, diabetes medication, and some blood pressure medication. It can also increase the risk of falls, confusion, low blood sugar, stomach irritation, and poor judgement.
Patients should ask their doctor or pharmacist whether alcohol is safe with their current medication list.
Do: Be Honest at Follow-Up Appointments
Patients should feel safe telling their bariatric team whether they drink alcohol and how often. The purpose is not to judge. The purpose is to protect the patient’s health, weight-loss outcome, nutrition, and long-term safety.
Bariatric teams are encouraged to screen for alcohol and substance use both before and after surgery, including long-term follow-up.
A simple honest statement is enough:
“I have started having wine again occasionally. Is that okay with my procedure and my current progress?”
“I feel alcohol much faster now. Is that normal?”
“I am worried that alcohol is affecting my eating plan.”
These conversations are part of responsible aftercare.
Practical Do’s and Don’ts After Bariatric Surgery
Do
Wait until your bariatric team clears you.
Treat alcohol as stronger than it was before surgery.
Start with a very small amount if you are cleared to drink.
Drink slowly.
Avoid driving after any alcohol.
Choose low-sugar, non-carbonated options where appropriate.
Prioritise protein, hydration, vitamins, and follow-up care.
Be honest with your medical team about alcohol use.
Stop if alcohol affects your food choices, hydration, mood, or weight-loss progress.
Don’t
Do not drink during early recovery unless your surgeon says it is safe.
Do not assume your old tolerance still applies.
Do not drink on an empty stomach.
Do not drink quickly.
Do not use alcohol to cope with stress, sadness, boredom, or anxiety.
Do not choose sugary cocktails, shots, or carbonated drinks as a habit.
Do not drive after drinking, even after a small amount.
Do not ignore changes in your relationship with alcohol.
Alcohol after bariatric surgery is not automatically forbidden for every patient forever, but it is never “business as usual.” After gastric bypass or sleeve gastrectomy, alcohol can affect the body faster, more strongly, and for longer than it did before surgery. It can also interfere with hydration, nutrition, weight loss, blood sugar control, and long-term health goals.
The safest approach is simple: wait until your bariatric team clears you, drink very cautiously if you choose to drink, avoid high-risk situations, and keep your health goals first.
References
- American Society for Metabolic and Bariatric Surgery. Life After Bariatric Surgery. The ASMBS notes that alcohol is absorbed more quickly after surgery and that bariatric patients may have higher alcohol levels for longer after drinking.
- Sogg S. Managing Substance Use Issues Before and After Metabolic and Bariatric Surgery. Bariatric Times. 2022;19(8):8-11. This article discusses substance-related screening, alcohol absorption changes after gastric bypass and sleeve gastrectomy, and the need for long-term postoperative education and monitoring.
- World Health Organization. Alcohol Fact Sheet. WHO describes alcohol as containing ethanol, a psychoactive and toxic substance with dependence-producing properties.
- CDC. Alcohol Use and Your Health. CDC explains excessive alcohol use and its health risks.
- MedlinePlus. Alcohol. MedlinePlus explains that alcohol is a central nervous system depressant that can affect mood, behaviour, memory, thinking, coordination, and physical control.

Practical Questions to Ask Before Bariatric Surgery

Bariatric surgery is a major medical decision.
It can support significant weight loss and improve obesity-related health conditions, but it also requires long-term commitment.
That is why your first consultation should not feel rushed.
It should help you understand your options, your risks, your expected results, and your responsibilities after surgery.
The goal is not to ask as many questions as possible.
The goal is to ask the right questions.
A prepared patient usually makes better decisions and has clearer expectations.
What to Bring to Your Bariatric Consultation
Before your appointment, gather the information your bariatric team may need.
This helps the surgeon and support team assess your health properly.
Bring the following if available:
- A list of your current medication
- Your weight history
- Previous diet attempts
- Previous weight-loss medication use
- Diabetes results, if relevant
- Blood pressure history
- Sleep apnoea diagnosis or symptoms
- Reflux or heartburn symptoms
- Details of previous operations
- Medical aid or insurance information
- Your
Continue writing please
personal goals for surgery
You do not need to have every answer before the consultation.
The purpose of the appointment is to help you understand what is medically suitable for you.
Questions About Procedure Choice
Not every patient needs the same operation.
The most suitable procedure depends on your weight, medical history, eating patterns, reflux symptoms, diabetes status, and long-term health goals.
Useful questions include:
- Which procedure do you recommend for me, and why?
- Why would you not recommend the other options?
- Am I better suited to sleeve gastrectomy or gastric bypass?
- How will reflux or heartburn affect the decision?
- How will diabetes affect the decision?
- What weight loss range is realistic for me?
- What are the main risks for my specific health profile?
- What happens if I do not lose enough weight?
- What happens if I regain weight later?
- Will I need a scope, blood tests, or scans before surgery?
A good answer should be specific to you.
If the answer sounds general, ask for more detail.
You should understand why a specific procedure is being recommended before you agree to it.
Questions About Safety and Risk
Bariatric surgery is commonly performed, but it is still major surgery.
You have the right to understand both common risks and serious risks.
Ask your surgeon:
- What are the most common complications?
- What are the serious but less common complications?
- What is my personal risk level?
- How do my age, BMI, diabetes, smoking history, or other conditions affect my risk?
- How do you reduce the risk of blood clots?
- How do you reduce the risk of leaks?
- What symptoms should I watch for after surgery?
- Who do I contact after hours if I am worried?
- What happens if I need to be readmitted?
- How often do complications happen in your practice?
Do not be afraid to ask direct questions.
A responsible bariatric team will explain risks clearly.
They will also explain what they do to reduce those risks.
Questions About Recovery
Recovery is different for every patient, but you should have a clear idea of what to expect.
Ask:
- How long will I stay in hospital?
- When can I walk after surgery?
- When can I drive?
- When can I return to work?
- When can I exercise again?
- What pain is normal?
- What pain is not normal?
- What should I do if I cannot keep fluids down?
- How long will I need help at home?
- When will my follow-up appointments take place?
Many patients focus only on the operation.
Recovery planning is just as important.
Arrange transport, time off work, help at home, and follow-up appointments before surgery.
Questions About Eating After Surgery
Your eating pattern will change after bariatric surgery.
This is not only about eating less.
It is about eating differently.
Ask your dietitian or surgeon:
- What will I eat in the first week?
- When do I move from liquids to soft foods?
- When can I eat normal textured food again?
- How much protein do I need each day?
- How much water should I drink?
- Can I drink tea or coffee?
- When can I drink alcohol again?
- What foods are most likely to cause discomfort?
- What happens if I eat too quickly?
- What should I do if I vomit often?
Eating after surgery is a skill.
You may need to learn smaller portions, slower eating, better protein choices, and proper hydration.
This adjustment takes time.
Questions About Vitamins and Supplements
After bariatric surgery, vitamin and mineral supplements are usually required.
This is especially important after gastric bypass.
Ask:
- Which supplements will I need?
- Will I need them for life?
- How often must I do blood tests?
- Which deficiencies are most common?
- How will I know if I am low in iron, B12, calcium, or vitamin D?
- Can I use ordinary pharmacy multivitamins?
- What happens if I stop taking supplements?
- Are injections ever needed?
- What symptoms should I report?
Do not wait until you feel unwell before checking your levels.
Nutritional deficiencies can develop slowly.
Regular follow-up helps detect problems early.
Questions About Cost and Medical Aid Cover
Bariatric surgery can involve several separate costs.
These may include the surgeon, anaesthetist, hospital, assistant surgeon, dietitian, psychologist, blood tests, scans, and follow-up care.
Ask for a written breakdown.
Important questions include:
- What is included in the quoted fee?
- What is excluded?
- Are hospital fees included?
- Is the anaesthetist included?
- Are dietitian consultations included?
- Are psychologist consultations included?
- Are blood tests included?
- Are follow-up visits included?
- What does medical aid cover?
- Is pre-authorisation required?
- What motivation documents are needed?
- What happens financially if there is a complication?
- What monthly costs should I expect after surgery?
A lower upfront price is not always cheaper.
Good follow-up can prevent expensive problems later.
Questions About Weight Loss Expectations
Patients often want to know how much weight they will lose.
That is understandable.
But no surgeon can promise an exact number.
Ask:
- What is a realistic weight-loss range for me?
- How much weight do patients usually lose after this procedure?
- How quickly does weight loss usually happen?
- When does weight loss slow down?
- What affects my final result?
- What happens if I lose less than expected?
- How do you monitor progress?
- Do you track body composition, or only weight?
- What role does exercise play?
- How do I avoid losing too much muscle?
The scale is only one measure.
Improved blood sugar, better mobility, lower blood pressure, reduced medication, and better sleep may also show progress.
Questions About Weight Regain
Weight regain can happen after any obesity treatment.
It can happen after medication.
It can happen after surgery.
That does not mean the patient has failed.
It means the cause must be assessed.
Ask:
- How common is weight regain after this procedure?
- When does regain usually happen?
- What are the main causes?
- How do you investigate weight regain?
- Can medication be used after surgery?
- Can the stomach stretch?
- When is revision surgery considered?
- Do you offer dietitian support if regain starts?
- Do you offer psychological support if emotional eating returns?
- What early warning signs should I watch for?
The best bariatric programmes plan for weight regain before it happens.
They do not shame patients.
They treat weight regain as a medical and behavioural issue that needs proper support.
Questions About Diabetes, Blood Pressure, and Other Conditions
Many patients choose bariatric surgery because of health problems linked to obesity.
These may include type 2 diabetes, hypertension, sleep apnoea, fatty liver disease, reflux, infertility, or joint pain.
Ask:
- How may surgery affect my diabetes?
- Could my diabetes go into remission?
- Will I need less medication?
- How soon can blood sugar improve?
- Who will adjust my diabetes medication?
- How may surgery affect my blood pressure?
- Will sleep apnoea improve?
- Should I keep using my CPAP machine?
- How will reflux affect my procedure choice?
- How will my liver health be assessed?
Do not stop medication on your own.
Some conditions improve quickly after surgery.
Medication changes must be supervised by your doctor.
Questions About Mental and Emotional Readiness
Bariatric surgery changes eating habits, body size, routines, confidence, and relationships.
Some changes are positive.
Some can feel difficult.
Ask:
- Do I need a psychological assessment?
- What does the assessment involve?
- How does emotional eating affect surgery results?
- What if I binge eat?
- What if I eat when stressed?
- What support is available after surgery?
- Can body image change after weight loss?
- How do patients usually cope with loose skin?
- What if I feel anxious before surgery?
- What if I feel low after surgery?
Mental readiness does not mean being perfect.
It means being honest about habits, triggers, support needs, and expectations.
Questions About the Bariatric Team
Bariatric surgery should not be a once-off transaction.
It should involve a team.
Ask:
- Who will be part of my care team?
- Will I see a dietitian before and after surgery?
- Will I see a psychologist if needed?
- Who manages my diabetes medication?
- Who checks my blood results?
- Who do I contact if I struggle with food?
- Who do I contact if I regain weight?
- How long do you follow patients after surgery?
- Do you offer group support or patient education sessions?
The quality of the team matters.
Surgery is the start of treatment, not the end.
A prepared patient usually makes better decisions and has clearer expectations.
Patient Checklist Before You Decide
Before agreeing to bariatric surgery, make sure you can answer these questions:
- Do I understand the procedure being recommended?
- Do I know why this procedure is best for me?
- Do I understand the risks?
- Do I understand the recovery process?
- Do I know what I will eat after surgery?
- Do I know which supplements I will need?
- Do I understand the cost?
- Do I know my follow-up schedule?
- Do I know who to contact if I have problems?
- Do I understand that long-term results require long-term care?
If you cannot answer these yet, ask for another consultation.
Taking more time before surgery is better than feeling unsure afterwards.
The Bottom Line…
Bariatric surgery can be a powerful treatment for obesity and related health conditions.
But the operation is only one part of the process.
- The best results usually come from careful preparation, realistic expectations, skilled surgery, structured aftercare, and long-term support.
- Before choosing surgery, ask clear questions.
- Understand your options.
- Know your risks.
- Plan your recovery.
- Commit to follow-up.
An informed patient is not being difficult. An informed patient is being responsible.

Behind the counter: Glucagon-like peptide-1 receptor agonists for type 2 diabetes
People with type 2 diabetes have a variety of options to manage the condition, including taking prescription drugs and making lifestyle changes. Glucagon-like peptide-1 receptor agonists (GLP-1 agonists) are one option.
In this article, Dr. Maria Prelipcean explains how GLP-1 agonists work, their benefits and risks, and some common side effects.
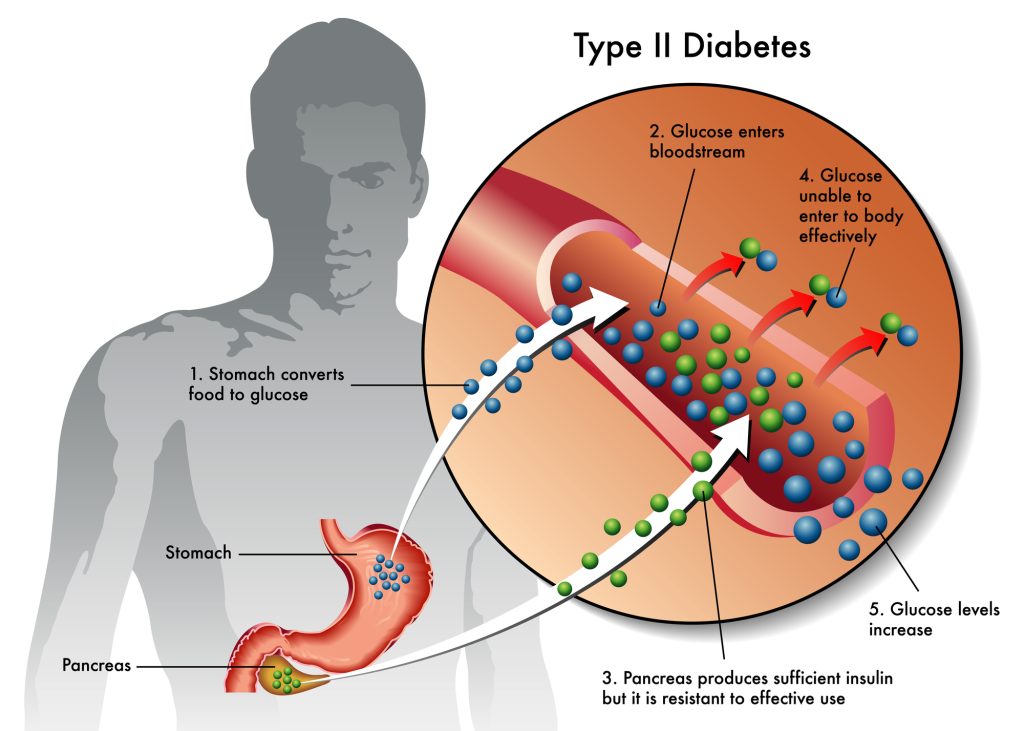
She also discusses the long-term risks for people who do not manage their type 2 diabetes effectively, along with some lifestyle changes that can make a difference.
What are GLP-1 agonists? How do they treat type 2 diabetes?
A doctor may prescribe GLP-1 agonists to help a person manage their type 2 diabetes.
GLP-1 agonists are a class of drugs that people use to manage type 2 diabetes.
GLP-1 is an incretin, which is one of the gut hormones involved in blood sugar control. GLP-1 agonists help reproduce or enhance the effects of this naturally occurring hormone.
GLP-1 agonists work in several ways, such as by:
- stimulating meal-dependent insulin secretion by the pancreatic beta cells
- decreasing the secretion of glucagon, a hormone that raises blood sugar
- decreasing gastric emptying
- decreasing appetite and reducing food intake by creating a sensation of stomach fullness
GLP-1 agonists may also have some direct effects on brain hunger centers. Since they decrease appetite, they may also help with weight loss.
Their main effect is to decrease spikes in blood sugar after eating. They have a smaller effect on fasting blood sugar levels.
They act mainly on insulin the body produces when a person eats a meal. This means that they are less likely to cause hypoglycemia if a person uses them in isolation, without other medications. However, people more commonly use GLP-1 agonists in combination with other medications for type 2 diabetes.
By themselves, they tend to reduce the glycohemoglobin by 0.5 to 1.2%. Glycohemoglobin is what an A1C test measures. Longer-acting types of GLP-1 agonist tend to reduce A1C levels slightly better.
Beyond managing blood sugar, do GLP-1 agonists have other potential benefits?
GLP-1 agonists do not cause hypoglycemia. This is a significant advantage compared with other antidiabetic drugs.
They also do not cause weight gain. They may even contribute to weight loss, in the range of 1.5 to 3 kilograms. However, this amount varies depending on factors such as lifestyle or the use of other medications.
GLP-1 agonists may also have beneficial effects for heart and kidney health.
Researchers have investigated outcomes for people with type 2 diabetes who take GLP-1 agonists. They found that people who also had heart disease or heart disease risk factors had fewer cardiovascular complications than placebo groups when they took one of the following GLP-1 agonists:
- liraglutide (Victoza)
- semaglutide (Ozempic)
- dulaglutide (Trulicity)
Evidence suggests that all three of these drugs also reduce the progression of kidney disease in people at high cardiovascular risk.
What is the difference between ‘short-acting’ and ‘long-acting’ GLP-1 agonists?
GLP-1 agonists are either “short-acting” or “long-acting,” depending on their dosing schedule and duration of action.
A healthcare provider will recommend a specific medication based on factors such as patient preference, their experience with prior therapies, convenience, and insurance coverage. Currently, no comparative trials demonstrate how choice of medication impacts long-term outcomes.
Short-acting GLP-1 agonists have twice per day dosing. They tend to have a greater effect on after-meal blood sugars and gastric emptying, and a lesser effect on fasting glucose.
One example of a short-acting GLP-1 agonist is exenatide (Byetta).
Long-acting GLP-1 agonists have once-daily or once-weekly dosing. They have a more marked effect on fasting glucose. They may also be slightly more effective at reducing A1C results.
Some examples of long-acting GLP-1 agonists include:
- liraglutide (Victoza), which people take once daily
- semaglutide (Rybelsus), which people take once daily
- dulaglutide (Trulicity), which people take once weekly
- semaglutide (Ozempic), which people take once weekly
- exenatide (Bydureon), which people take once weekly
When do healthcare providers recommend GLP-1 agonists? Can people combine them with other diabetes medications?
The first medication that most people with type 2 diabetes use is metformin. Their doctor may also recommend making lifestyle changes.
However, type 2 diabetes is a progressive condition. Over time, most people will need to use additional therapies. People who experience severe side effects or other issues when they take metformin may also switch to GLP-1 agonists.
GLP-1 agonists may be a better choice when either weight loss or avoiding hypoglycemia is a priority. Healthcare providers may also recommend them for people with elevated postprandial blood sugars.
People with heart disease or heart disease risk factors are also good candidates for this therapy.
In most cases, injectable GLP-1 agonists can reduce blood sugar levels as much as daily insulin injections. People who are interested in GLP-1 agonists but who want to avoid injections could talk to their doctor about an oral form called semaglutide (Rybelsus) that recently became available.
Doctors primarily prescribe GLP-1 agonists in combination with other diabetes medications. The best combination of treatments for any person depends on many factors, including any other conditions they have, their own preferences, and cost concerns.
What are the most common side effects of GLP-1 agonists?
The most common side effects are gastrointestinal. Nausea, vomiting, and diarrhea can occur in many people. Nausea may improve with time and a lower dose. Also, it may occur less often with the weekly types of medication.
Some reports link acute pancreatitis with GLP-1 agonists, but there are not enough data to establish a clear causal relationship. If a healthcare provider suspects pancreatitis, a person should stop the drug and not restart it.
Researchers continue to investigate other possible adverse effects on the pancreas. For example, one group explored whether or not there could be a link between GLP-1 agonists and pancreatitis, as well as pancreatic cancer, but it did not find sufficient evidence of a linkTrusted Source.
Some GLP-1 agonists may cause local skin reactions at the injection site. For example, people using exenatide (Bydureon, Byetta) have reported this side effect.
Hypoglycemia rarely occurs with GLP-1 agonists when a person uses them alone or alongside metformin. However, adding them to insulin-based therapies can increase the risk.
What are the long-term risks of not managing type 2 diabetes effectively?
Diabetes carries an increased risk of complications involving the blood vessels. These are called microvascular and macrovascular complications.
Microvascular complications involve damage to the small blood vessels of the eyes, kidneys, and peripheral nerves. In turn, this leads to retinal damage, chronic kidney disease, and neuropathy.
The damage can be serious. For example, diabetes is one of the leading causes of blindness. It is also the most common cause of end stage kidney disease requiring dialysis.
Treatment makes a difference. A landmark study from 1998 showed that intensive diabetes therapy was associated with a 25% decrease in microvascular complications.
Diabetes also increases the risk of damage to large blood vessels (macrovascular disease) in the heart, brain, and legs. This type of damage increases the risk of heart attacks, strokes, peripheral vascular disease, infections, and amputations.
Managing diabetes effectively by keeping blood sugars within a healthy range makes a big difference in lowering the risk of these complications. It also helps address other risk factors for blood vessel problems.
To manage diabetes, healthcare providers will also encourage people to:
- stop smoking
- lose weight, if necessary
- address high blood pressure, with lifestyle changes or medication
- manage cholesterol levels, with lifestyle changes or medication
People who experience episodes of high blood sugar or severely low blood sugar can also experience serious complications. However, with proper monitoring and an individualized treatment plan, most people can prevent these complications or reduce how often they occur.
What else do people need to know if they are considering starting GLP-1 agonists?
It is important for people to listen to their healthcare provider’s advice when it comes to their treatment plan.
People with a history of pancreatitis should not use GLP-1 agonists. Also, no one with a history of decreased kidney function should use the GLP-1 agonists Byetta or Bydureon.
Based on animal models, people should not use these medications if they have a personal or family history of certain health conditions, including medullary carcinoma of the thyroid or multiple endocrine neoplasia type 2.
Like any other diabetes medication, GLP-1 agonists should be part of a comprehensive individualized treatment plan. The goal of the treatment plan is to keep blood sugar levels in a healthy target range and manage overall health.
Are there any lifestyle changes that may help people with type 2 diabetes?
People with type 2 diabetes should make it a top priority to lower their risk of heart disease. This means following heart-healthy habits, along with managing blood pressure and cholesterol levels.
Depending on the individual, lifestyle changes may include:
- modifying their diet
- quitting smoking
- losing 5–10% of their body weight, for those who have overweight or obesity
- exercising for 150 minutes each week
Healthcare providers may also recommend that people manage cholesterol levels using statin medications.
Self-monitoring of blood sugar levels also improves blood sugar management. Individuals can use a fingerstick method or a continuous glucose monitor.
Seeing a dietitian may help with eating a more healthful diet. A dietitian can recommend an individualized nutrition plan that accounts for a person’s preferences and needs.
In general, when it comes to diet, people may improve their blood sugar management by reducing their intake of carbohydrates, saturated fats, and alcohol and using the diabetes plate method as basic guidance for meal planning.
Medication may also help with weight management in some cases.
When a person has very high blood sugar levels or other symptoms of type 2 diabetes, they need to use insulin. Making lifestyle changes as soon as possible, and sticking with them, may help people prevent the need for additional medication.
Source Credit: https://www.medicalnewstoday.com/articles/glp-1-receptor-agonists-type-2-diabetes?utm_source=ReadNext#lifestyle-changes

Dyspepsia (Indigestion): What It Is, What Causes It, and What to Do
Indigestion is one of those everyday problems that can feel minor… until it keeps coming back. The medical term for indigestion is dyspepsia, which simply means a collection of uncomfortable symptoms in the upper stomach area.
In this guide, we’ll explain dyspepsia in plain language, what to watch out for, and what typically helps
What does dyspepsia feel like?
Dyspepsia often includes one or more of the following symptoms:
- Upper stomach pain or discomfort
- Bloating or feeling uncomfortably full after eating
- Feeling full quickly (even after small meals)
- Belching, regurgitation, or a “sour water” feeling in the mouth
- Heartburn or burning behind the breastbone
- Nausea or vomiting
- Retrosternal (chest-area) burning
A quick note: “organic” vs “functional” dyspepsia
Doctors usually group dyspepsia into two broad types:
Organic dyspepsia means there’s a clear cause, such as:
- Peptic ulcers
- Acid reflux (GERD)
- Less commonly, upper GI cancers
Functional dyspepsia means symptoms are real, but tests don’t show a clear structural problem. It may be linked to diet, stress, and lifestyle.
Dyspepsia is common—but persistent symptoms should be assessed properly so serious causes aren’t missed
Red flags: when indigestion needs urgent medical attention
Some symptoms increase the chance of a serious underlying problem. If you have any of the below, don’t self-treat—see a doctor promptly.
Alarm features include:
- Age 50 or older (especially if symptoms are new)
- Difficulty or pain when swallowing
- Vomiting blood, passing black stools, or any GI bleeding
- Unexplained weight loss
- Iron deficiency (with or without anaemia)
- A palpable abdominal mass
- Severe or persistent abdominal pain
- Regular use of ulcer-causing meds like NSAIDs (e.g., ibuprofen, diclofenac)
- Strong family history of upper GI cancer or relevant genetic syndromes
If you’re under 50 with no red flags: the usual starting approach
When someone is under 50, has no alarm features, and no concerning medical history, management often starts with a “low-risk” pathway.
1) Test for H. pylori
Helicobacter pylori is a common stomach infection that can cause inflammation and ulcers. Recommended non-invasive tests include:
- Urea breath test, or
- Stool antigen test
Important: In high-prevalence settings like South Africa, blood (serology) tests are not recommended because they may not reliably show active infection.
2) Try acid-reducing treatment (PPI trial)
A proton pump inhibitor (PPI) reduces stomach acid and can help symptoms settle. A typical trial is 6–8 weeks.
3) If H. pylori is positive, treat it
If the test is positive, eradication therapy is recommended.
4) Reassess
If symptoms persist or return after initial treatment, the guidance recommends upper endoscopy (a camera test of the oesophagus and stomach).
When is an endoscopy recommended upfront?
If you are 50+, have alarm features, or have persistent symptoms, an upper endoscopy is recommended to look for ulcers, erosions, growths, or other causes.
Practical lifestyle tips that often help (for everyone)
These everyday changes are recommended in all cases of dyspepsia:
- Avoid common trigger foods (often citrus, tomatoes, chocolate, spicy, fatty/fried foods)
- Eat smaller meals more often
- Choose lower-acid foods where possible
- Stay hydrated
- Maintain a healthy weight
- Avoid tight clothing around the stomach
- Elevate the head of the bed if night symptoms are a problem
- Don’t lie down for 2–3 hours after eating (avoid late-night meals)
- Manage stress (breathing exercises, meditation, relaxation)
- Avoid smoking
- Limit caffeine and alcohol
- Avoid fizzy drinks if they worsen bloating
Over-the-counter and prescription options (simple explanation)
Antacids (fast, short-term relief)
Antacids neutralise stomach acid and can help heartburn, indigestion, and bloating. Common ingredients include calcium carbonate, magnesium hydroxide, or aluminium hydroxide.
They can have side effects (like diarrhoea or constipation) and may interact with other medicines—so if you’re using them often, get checked.
Acid suppression (stronger symptom control)
Acid-suppressing medicines reduce acid production and can be very effective.
- PPIs are often first-line for dyspepsia (examples include esomeprazole, lansoprazole, pantoprazole, rabeprazole).
Long-term PPI use should be reviewed with a clinician due to potential risks.- H2 blockers can help mild-to-moderate symptoms (e.g., famotidine, cimetidine, nizatidine). Ranitidine has been withdrawn for safety reasons.
H. pylori treatment and follow-up (the important bits)
Treatment uses combinations of acid suppression + antibiotics (and sometimes bismuth), and the exact regimen depends on local resistance patterns and prior treatment.
Confirming eradication matters: a urea breath test or stool antigen test is used at least 4 weeks after treatment ends to confirm the infection is cleared.
Frequently asked questions (FAQ)
“Is indigestion always caused by acid?”
Not always. Dyspepsia can be linked to reflux/acid, ulcers, H. pylori, certain medications, diet, and stress.
“If a PPI helps, do I still need tests?”
If you have red flags or are 50+, an endoscopy is recommended to rule out more serious issues.
“When should I stop self-treating?”
If symptoms are persistent, worsening, or you’re relying on antacids/acid reducers frequently—or you have any alarm features—get assessed.
Key takeaways
- Dyspepsia is common and often treatable.
- Red flags (especially age ≥ 50, bleeding, weight loss, swallowing problems, anaemia/iron deficiency) should be checked urgently.
- Low-risk patients typically start with H. pylori testing and/or a PPI trial, plus lifestyle changes.
Source Credit: SAJGH_SAGES_dyspepsia_guidance
Gastric bypass (Roux-en-Y)
Gastric bypass, also called Roux-en-Y (roo-en-wy) gastric bypass, is a type of weight-loss surgery that involves creating a small, egg-sized pouch from the stomach. The newly created pouch is then connected directly to the small intestine. After gastric bypass, swallowed food goes into this small stomach pouch and then directly into the small intestine, thereby bypassing most of the stomach and the first section of the small intestine.
Gastric bypass is one of the most commonly performed types of bariatric surgery. Gastric bypass is done when diet and exercise haven’t worked or when you have serious health conditions because of your weight.
Roux-en-Y Gastric Bypass
Why it’s done
Gastric bypass is done to help you lose excess weight and reduce your risk of potentially serious health issues, including:
- Gastroesophageal reflux disease.
- Heart disease.
- High blood pressure.
- High cholesterol.
- Obstructive sleep apnea.
- Type 2 diabetes.
- Steatotic liver disease, formerly known as fatty liver disease.
- Stroke.
- Cancer.
- Infertility.
- Urinary incontinence.
- Joint pain.
Gastric bypass is typically done only after you’ve tried to lose weight by improving your diet and exercise habits.
Who is a candidate
In general, gastric bypass and other weight-loss surgeries may be an option for you if:
- Your body mass index (BMI) is 40 or higher.
- Your BMI is 35 to 39.9, and you have a serious weight-related health condition, such as type 2 diabetes, high blood pressure or severe sleep apnea. In some cases, you may qualify for certain types of weight-loss surgery if your BMI is 30 to 34 and you have serious weight-related health conditions.
But gastric bypass isn’t for everyone who is severely overweight. You may need to meet certain medical guidelines to qualify for weight-loss surgery. You likely will have a screening process to see if you qualify.
You must also be willing to make permanent changes to lead a healthier lifestyle. You may be required to participate in long-term follow-up plans that include monitoring your nutrition, your lifestyle and behavior, and your medical conditions.
Check with your health insurance plan or your Medical Aid to find out if your policy covers weight-loss surgery.

Prescription drug monitoring needed after weight loss surgery
People who have had weight loss surgery may need closer monitoring of their prescription medication to avoid risk of harm, researchers at King’s College London have found.

The study, published in the British Journal of Clinical Pharmacology, found that bariatric surgery patients face unique risk factors relating to overdose. This is because the surgical changes to their stomach and intestine to reduce food and nutrient absorption may also affect how they absorb drugs.
By examining data from the National Programme of Substance Use Mortality (NPSUM), the researchers conducted the first toxicology-based investigation of overdose deaths in post-bariatric surgery patients.
Multiple medications – including opioids, antidepressants and common painkillers – were detected at post-mortem in every case, and often included medications that the deceased were not actively prescribed. Opioids were found to have contributed to the deaths of nearly every person, while antidepressants were implicated in the deaths of just under half. Unlike many cases on the NPSUM database, illicit drug and alcohol use was rare. Together, this highlights how chronic pain and mental health conditions leave this group particularly vulnerable to prescription-medication harm.
Our research highlights a gap in care that is readily addressable. Post-bariatric surgery patients are frequently seen by their clinicians in routine follow-up appointments, into which advice about drug safety could be integrated. Embedding pharmacist-led medication reviews into standard follow-up could prevent avoidable overdose deaths in this vulnerable group.”Dr Caroline Copeland, Senior Lecturer in Pharmacology & Toxicology, King’s College London
Bariatric surgery is a group of surgical operations that help people lose weight by changing the stomach and sometimes the small intestine. Some surgeries, such as a gastric sleeve, reduce the size of the stomach by 70 – 80% so it can hold much less food. Others, including gastric bypass, reroute or bypass parts of the small intestine, allowing less food to be absorbed.
While bariatric surgery can be a powerful tool in reducing excess weight, previous studies have highlighted how these significant surgical changes can unpredictably alter the pharmacokinetics of gastrointestinal system, influencing how drugs are absorbed. While this differs from person to person – depending on the type of surgery, the drug involved, and other factors – these pharmacokinetic changes can increase the potency of drugs, or alternatively, decrease the potency, leading to repeated dosing.
The researchers identified 18 people with a history of bariatric surgery whose deaths were noted in the NPSUM records between 1997 and 2025. Coroners voluntarily report a death to NPSUM if psychoactive drugs were detected or implicated in causing the death, or if the deceased had a history of drug use.
Opioids were detected and contributed to the deaths of 94.4% (17 out of 18) of cases, compared to an average of just 67% across all 58,000 cases on the NPSUM database. Non-opioid analgesics, which include drugs such as paracetamol and ibuprofen, were found in 72.2% (13/18) of cases. The prevalence of these medications suggest that this patient group faces chronic pain and has risks around medication to manage this.
Depression and anxiety were common in this group, and antidepressants were identified in 83.3% (15/18) of cases and found to have contributed in just under half of deaths.
The combination of mental health diagnoses and chronic pain suggest polypharmacy – when an individual is on multiple medicines at once – could be a problem, leading to higher risk of side effects and drug interactions. The average number of drugs detected at post-mortem was six.
Coroners had determined that 75% of individuals had died of accidental overdose. This closely aligns with the NPSUM database, where 76% of deaths are classified as accidental. However, while illicit drugs and alcohol frequently contribute to deaths in the wider NPSUM dataset, such involvement was rare among the post-bariatric surgery cases.
The researchers call for more work to be done to better understand how surgery changes the pharmacokinetics of the gastrointestinal system and therefore the way drugs are absorbed. They also suggest that a clinical pharmacist is involved in discussions before surgery takes place, and that drug monitoring continues for patients following their surgery.
It isn’t clear the extent to which healthcare providers in the UK include routine assessment of medicines before and after bariatric surgery. However, the deaths link to prescription medicines outlined in this study suggest that there is a need for this. Clinical pharmacists are in a good position to review medicines after bariatric surgery considering the ongoing changes in pharmacokinetics and how patients respond to drugs, their side effects, drug-drug interactions and other adverse drug reactions.”Dr Alice Oborne, Medicine Safety Lead, Guy’s and St Thomas’ NHS Foundation Trust
Source Credit:
www.kcl.ac.uk/news/prescription-drug-monitoring-needed-after-weight-loss-surgery
Dr Caroline Copeland
Senior Lecturer in Pharmacology & Toxicology

When Obesity and Depression Coexist — How to Manage Both
Kathleen Doheny
October 28, 2025
Obesity and depression are two of the most pressing public health challenges.

Globally, more than 280 million people live with depression, and 890 million adults live with obesity. When the conditions coexist, the challenge for clinicians becomes how to manage both successfully at the same time.
The relationship between the two conditions is likely bidirectional, experts agreed, and shared biological, psychological, and social pathways put patients at risk for both.
A patient with major depressive disorder has a 71% increased risk of developing obesity compared with someone who does not have that mental health diagnosis, according to a new report in The Lancet. People living with obesity have a 32% increased risk of developing depression compared with an individual not living with obesity.
When the conditions overlap, and clinicians need to manage both at once, where can they turn?
No Formal Guidelines for Comorbid Obesity, Depression
Unfortunately, they cannot turn to formal guidelines to address both at once because they do not exist.
While separate guidelines abound for obesity and for major depressive disorder, these same organizations, from obesity organizations to psychological, “don’t offer specific recommendations for those with both conditions,” said Pamela Kushner, MD, a clinical professor of family medicine at the University of California Irvine Medical Center in Orange, California. She co-authored a 2025 review of the literature and offered recommendations on treating obesity in patients with depression.
The Lancet reviewers agreed. Despite the high prevalence of major depressive disorder with comorbid obesity, there are no clinical guidelines for monitoring and managing this patient group, they wrote.

But these two recent literature reviews, along with another published this year from the Cleveland Clinic, do offer preliminary guidance on how to manage the conditions when they overlap. Here, some highlights of their recent reviews, along with additional input from the authors.
Lancet: A Risk Stratification and Monitoring Framework
It’s crucial for clinicians to recognize the double stigma patients may encounter when they are living with both obesity and depression, wrote co-author Nils Opel, MD, a psychiatrist at Charité-Universitatsmedizine Berlin in Berlin, Germany.
Guilt, shame, and helplessness are common, he said, leading people to put off doctor’s visits or skip them altogether. Psychiatrists might be the only point of contact for the patients, so they may have a role in not only mental health but also physical and metabolic health, the researchers wrote. Among their suggestions:
- Systemic screening is needed, including metabolic, lifestyle assessment; psychiatric evaluation; and assessment of demographic and psychosocial risk factors. It’s crucial to rule out underlying conditions, such as Cushing syndrome and obstructive sleep apnea, and other conditions. Metabolic assessment can include not only BMI but also assessment of waist circumference or waist-to-hip ratio.
- Ongoing monitoring is needed for obesity, metabolic dysregulation, poor lifestyle habits, body weight gain during a depressive episode, and treatment-resistant major depressive disorder. Poor diets, especially those high in simple sugars and processed snacks, raise the risk for weight gain and metabolic disturbances. Emotional eating is a frequent, and harmful, coping method. With the high risk for complications in this population, ongoing monitoring of changes in depressive symptoms and metabolic health is necessary.
- Treatment strategies include psychotherapy, antidepressant drugs, physical exercise, dietary interventions, and metabolic drugs. Research suggests that serotonergic medications are less efficient in these patients than those acting on noradrenergic or dopaminergic pathways. As an example, they wrote, higher response rates have been reported in those on selective serotonin reuptake inhibitors (SSRI) combined with adjunctive bupropion and in those treated with venlafaxine compared with SSRI alone.
- Whether the GLP-1 medications for weight loss may help depressive symptoms or worsen them is often discussed on social media, and the focus of this study that found differing opinions. Scientific evidence is scarce.
Needed: A Holistic Treatment Plan
With the overlap in the pathways underlying both diseases, a holistic treatment plan is needed, Kushner and her colleagues concluded.
Among their practical suggestions:
- Systemic inflammation is associated with depression, and obesity is linked with depression symptoms, such as fatigue and low energy.
- Primary care physicians should regularly screen patients for obesity and screen patients with obesity for depression.
- When considering treatment options for both conditions, consider how the interplay may affect treatment success. For instance, weight gain occurs with some antidepressants, so this must be taken into account. A table in their review lists numerous antidepressant options but only five with neutral weight effects or weight loss (bupropion, dextromethorphan-bupropion, esketamine, fluoxetine, and zuranolone). Likewise, anti-obesity medications have varying results, with losses of 5% to more than 20% produced.
If an antidepressant is indicated, “choose one that does not cause weight gain,” Kushner said in an interview with Medscape Medical News. While that may seem like common sense, she said, “I see so many patients on antidepressants known to cause weight gain.”
Kushner encourages her fellow primary care doctors to bring up the weight conversation. “Many clinicians are afraid to discuss obesity with their patients,” she said. They’re concerned, she said, about hurting patients’ feelings, “so they don’t even ask.” In her 30 years of primary care practice, she said, she is sure that approach is misguided. “They want to talk about it.”
Besides helping patients with obesity talk about their weight, and devise a plan, she said, it’s crucial to ask patients with obesity, especially women, about any history of childhood trauma, such as sexual and physical abuse. Numerous studies have found an association.
Treat Depression First?
In a review of recent studies on the interaction between obesity and depression, Cleveland Clinic researchers said research suggests treating depression first when both conditions occur together is beneficial.
Both conditions are pervasive and costly to treat, they noted, and are likely interacting to worsen patient outcomes.
Among the many mediating factors between obesity and depression, research suggests, is emotional eating.

Cognitive-behavioral therapies aimed at comorbid obesity and depression have demonstrated effectiveness, their review found. While weight loss didn’t improve in a 1-year study of cognitive-behavioral therapy, for instance, depression did, and improvement in depression is linked with weight loss.
“For most patients, depression and obesity can be treated concurrently, as improvement in one arena often have a positive effect on the other,” co-author Leslie J. Heinberg, PhD, vice chair of psychology at Cleveland Clinic, Cleveland, told Medscape Medical News.Depending on severity, however, one condition may need to be prioritized, she said. While a patient with severe depression may need psychiatric treatment first, a patient with very severe obesity may need interventions such as bariatric surgery first, for instance.
Successful Comanagement
Heinberg recalled an example of comprehensive care that produced good results. A patient, in his late thirties, had class III obesity and major depression, generalized anxiety disorder, binge eating disorder, and posttraumatic stress disorder.
The patient’s primary care clinicians prescribed an SSRI, tricyclic antidepressant for sleep, atypical antipsychotic for augmentation, and hydroxyzine. The patient had difficulty making changes to diet and had no insurance coverage for an injectable GLP-1.
“After a comprehensive evaluation by obesity medicine, psychology, and a dietitian, the patient was referred to a psychiatrist for a full evaluation and a number of less obesogenic medications were prescribed,” Heinberg said. The patient reported improved mood and started psychotherapy, also receiving group treatment for binge eating along with consultation from nutrition experts and initiation of naltrexone-bupropion.
Within a few months, improvement in mood continued, binge eating episodes remitted, and a 10% weight loss had occurred, Heinberg said.
Source Credit: https://www.medscape.com/viewarticle/when-obesity-and-depression-coexist-how-manage-both-2025a1000tar?form=fpf
Recent Comments